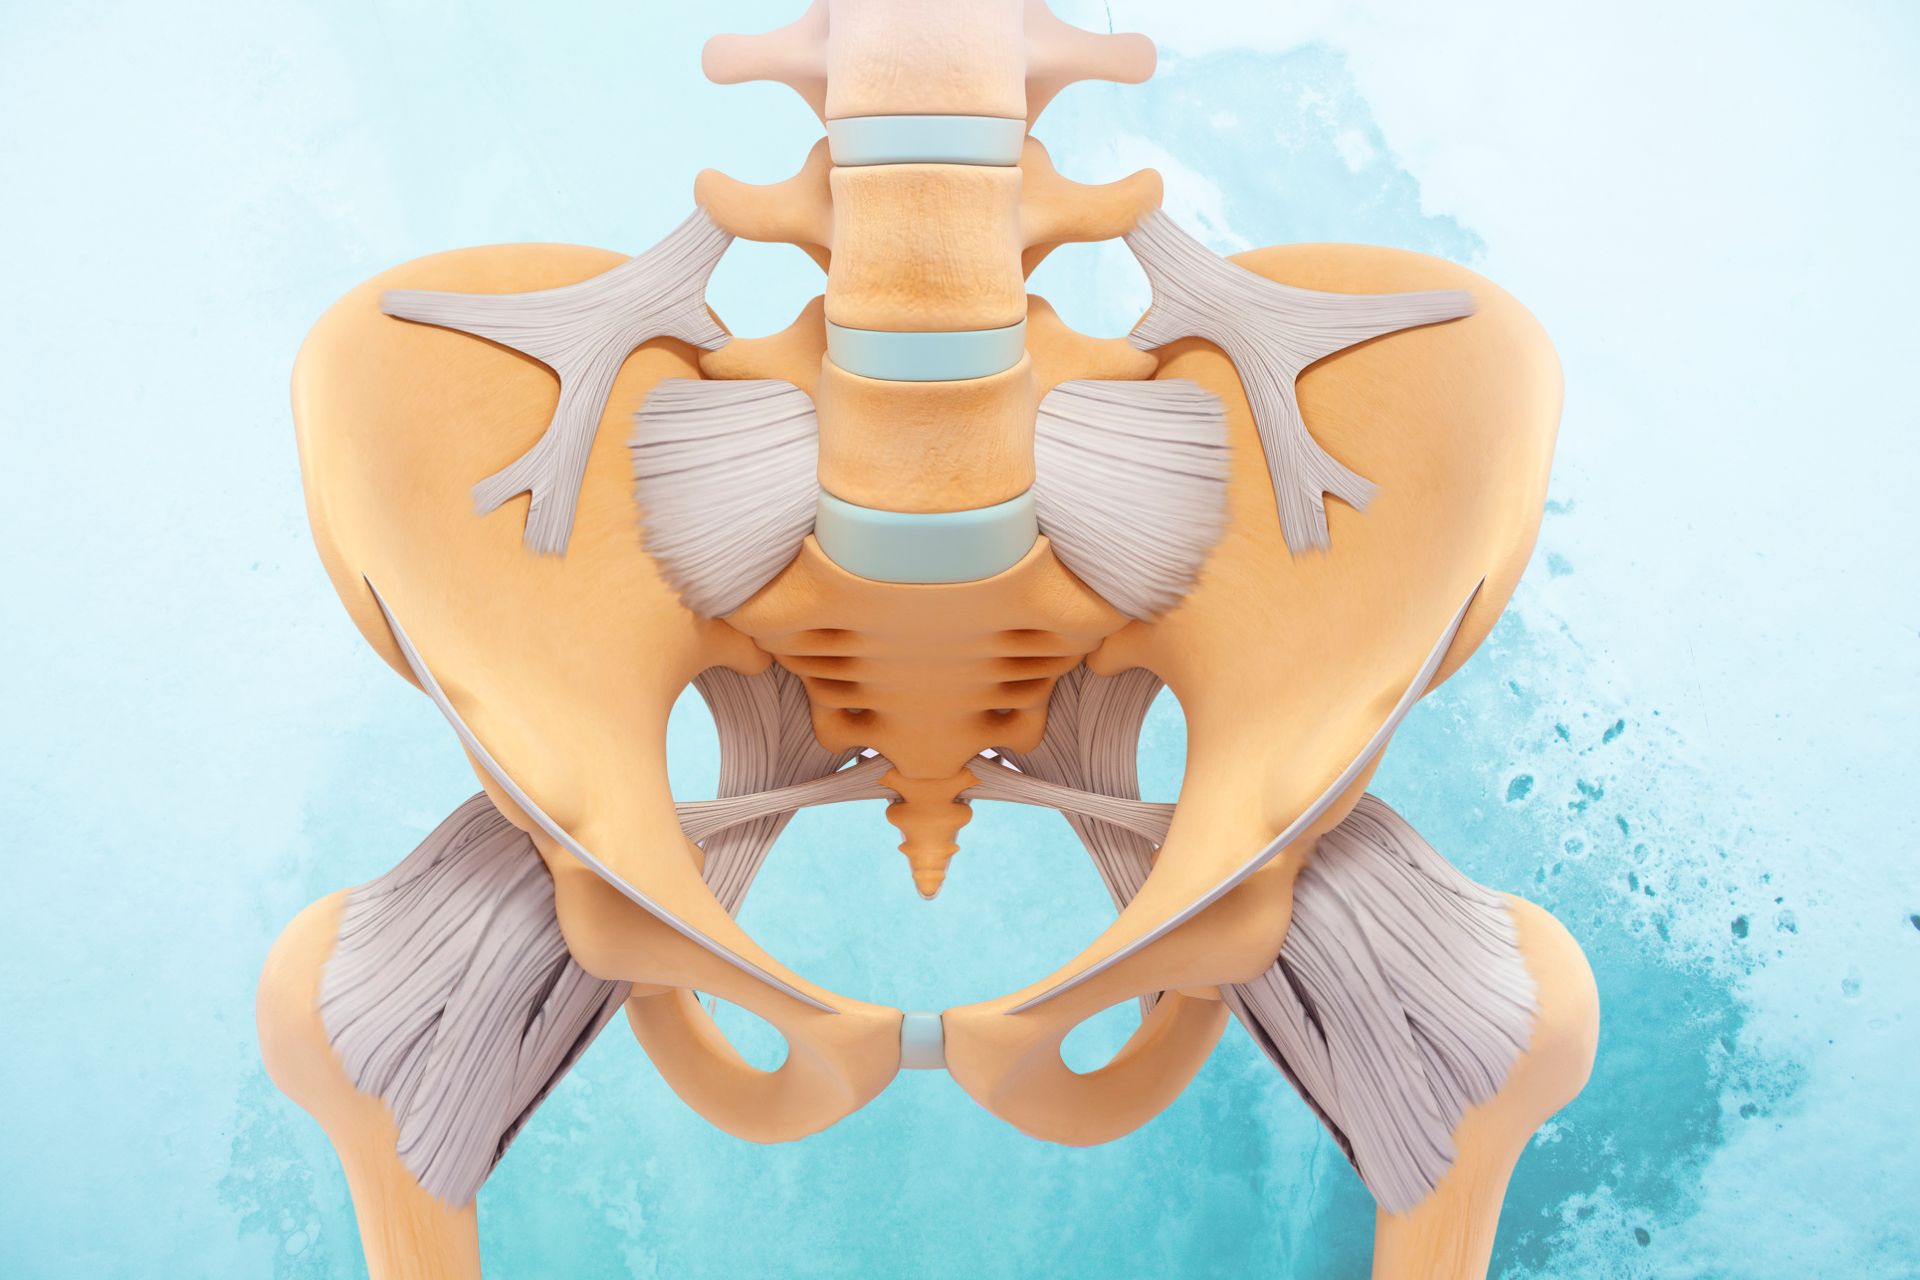
Ever wondered about your Pelvic Floor?

Guest blog by Kylie Royal Meehan from Fit Well You • October 4, 2022

It’s a funny thing when we discover that we have been wrongly conditioned to believe something about ourselves. And for me, that belief was actually about my Pelvic Floor!


Having a weak pelvic floor was something that had become so ingrained in me that in many ways it impacted how I trained, how frequently I was doing my pelvic floor exercises (too often!), as well as the frequency I was going to the bathroom pre-workout or long drive! 


As an Exercise Physiologist and Running Coach, Pelvic floor (PF) and core stability is a topic I discuss with clients, literally on a daily basis and almost exclusively the topic of ‘strengthening’ and training the pelvic floor (PF) complex. Despite being in the Health and Fitness Industry for over 20 years it has only been in recent months the concept of an ‘overactive pelvic floor’ has hit my radar and how it can affect your pelvic stability. You see, the majority of fitness professionals are trained and conditioned to believe the PF complex will be weak in almost everyone you see and all the cueing and information we are taught at uni and beyond is on how to work it in one direction - up! Lift, hold, count, repeat. We are always encouraging clients to hold in that wind, stop the flow of urine, to master the gold standard 10-second endurance hold. There was no consideration that these muscles could be overworked or could get stuck in a state of almost constant contraction! Naturally, if a muscle is already contracted there will be very little movement on assessment and thus presumed to be weak or underactive.


On reflection, there has been one occasion when I discovered the importance of being able to relax that pelvic floor and that was when I had a Physio assessment during my pregnancy back in 2018. During that appointment, I remember the Physio mentioning that “it would be a good idea to practice relaxing my PF as the chance of a tear during birth and long-term issues postpartum will be high. To be honest I don’t remember much in the way of technique instruction and really just tried to ignore the underlying fear I now had while I practiced a technique with no idea if I was doing it effectively. This fear became so ingrained in me that when I woke from the General Anaesthetic post-C-Section birth (it's a long story!!) my first memory is of doing my PF lifts. True story. I had gotten myself in quite a state about it and had secretly panicked about the birth for the remaining months of pregnancy. All the while I silently pleaded with these PF muscles to relax while no doubt clenching the crap out of them in my stress state! 


While this physio had in fact suggested the concept of relaxing these incredible muscles it was only provided in the context of being important during birth. Similarly, when I had my assessment post-birth by a different physio I was told my PF “wasn’t great, but it likely never had been” so continue with the daily PF endurance holds, bounces and glute squeezes. Sound familiar to anyone?


Now I am at no point suggesting these Physio’s did the wrong thing because I’m also a trained professional and I never questioned it either. I just continued believing that I was like many women - weak through the PF, that my years of running, endurance training and overzealous toileting habits had likely made it worse. I also didn't start to connect the dots that the niggling pelvic, tailbone, hip and glute injuries that started to occur within 6 months of birth may have been due to anything other than my own pelvic structure and hormones changing. 

What I am suggesting is that knowledge is power and that it is important to consider all that is going on rather than make a presumption that weakness of the PF is the only option. 


So here I am some hours after my appointment at Pelvic Health Melbourne feeling a combination of relief, direction, focus, awe, and just a little bit of frustration and embarrassment that I didn’t know all this sooner. So why did I book in for a Pelvic Health Assessment four years postpartum with no apparent PF issues or symptoms? Initially, the idea was solely to go for my own learning and development and to find out exactly what I would be referring my clients for! 

With a lot of PD occurring in the background of my life with a particular focus on Women’s Health it was only natural that I would start to link my learning to clients I was seeing and as fate would have it just recently I had been referred a patient who had torn a PF muscle during exercise due to it being hypertonic (muscle tightness/ increased tone). The more I read and researched in recent weeks the more I started pondering my own long-term hamstring and hip issues, particularly since having my daughter. By the time I arrived at my appointment I was almost excited to get confirmation that it was my pelvic floor causing a lot of my injury issues that despite long-term rehab would not go away. 


Again I will re-state - Knowledge is Power and in my appointment today I saw via Real Time Ultrasound and as well as a complex examination that my previous conditioning and belief were all wrong. My left side pelvic floor musculature is basically locked on and when attempting the lifts and holds it barely moves from its already elevated state. Because of this over-active muscle, the rest of my pelvis is being pulled in odd directions and it gives reason and explanation to almost every niggly injury and irritation that has presented over the past four years. It also explains why on many occasions I’ve struggled to pinpoint exactly where the pain was originating from… turns out I was trying to find it on the outside of my pelvis when all the while it was on the inside. 


So now I have a different type of rehab ahead of me, getting the muscles to release and relax using a combination of pressure release work and belly breathing techniques to encourage the pelvic diaphragm to work effectively.


So to wrap up and provide you with some practical takeaways… 


  • If you haven’t had a complex and in-depth Pelvic Health Assessment then book in now! Honestly, it is worth it. Pelvic pain, incontinence, instability, unexplained injuries, and prolapse are all treatable and they are surprisingly common, it's just that we don't talk openly about our issues! 
  • I 100% recommend Pelvic Health Melbourne and if there isn’t one near you they can advise on who to see in other areas. Email: info@pelvichealth.melbourne
  • If something doesn’t feel right for you or you have a chronic or ongoing niggly injury that won't rehabilitate, ask questions, think outside the box and follow your intuition. Don’t settle or ignore it and hope it will go away! 
  • If you had a C-Section you still need to be assessed! And if you are male you too may need to be assessed. Everyone can experience Pelvic Health issues. 
  • PF training should involve mastering both relaxations as well as contractions. It is not just about contracting and holding. 
  • Finally and somewhat shockingly Bluey, or more specifically Bandit was wrong about this. A tactical wee is actually not a good idea in the long term and can cause a number of issues. Crazy I know! 


If anything in this blog resonates with you please reach out and ask any questions you have. 

I am in no way affiliated with Pelvic Health Melbourne, nor do I receive any compensation or reward for recommending them. This is my honest opinion of the treatment I have received and I couldn’t be more impressed.


Blog re-posted with permission from Kylie Royal Meehan from Fit Well You. https://www.fitwellyou.com.au

Thank you Kylie


Kylie Royal Meehan - Fit Well You

A little about Kylie

Kylie is an advocate of wellness in every sense of the word!


Her passion for anything health, fitness and wellness is like a beacon but she also has a strong belief in balance and making the most of life’s opportunities!


Kylie has been in the industry since the late 90’s working as an Exercise Physiologist and Personal trainer as well as in high-level injury rehabilitation, with elite athletes at the AIS and NTIS and with the general population.


Kylie's aim is that her positive attitude and high level of motivation will rub off on her clients and they will live their best lives.

Qualifications: Accredited Exercise Physiologist, Level 2 Recreational Running Coach, Personal Trainer. 

Mental Health First Aid trained and Peer Support leader (Emergency services sector).


More from the blog

By Therese Stegley September 16, 2026
Putting in a tampon should not feel like you're fighting your own body. Yet for many people, tampon insertion can cause: Pain or burning A feeling of tightness Resistance or a “wall” Difficulty inserting it at all Pain when removing it Discomfort that lingers afterwards And often, the response is, “Just relax.” But if you've tried to relax and it still hurts, there's probably more to the story. Why can tampons hurt? There are many possible reasons. Painful tampon use can be associated with: Pelvic floor muscle tension Vaginal dryness Irritation or infection Skin or vulval conditions Hormonal changes Previous painful experiences Conditions affecting the vulva or vagina Sometimes more than one factor is involved. Could your pelvic floor be too tight? It could be. Your pelvic floor muscles surround the vaginal opening and need to relax to allow comfortable insertion. If these muscles are overactive or you're unconsciously tightening them, inserting a tampon can feel painful, difficult or even impossible. This can happen even if you are otherwise healthy. And importantly, a tight pelvic floor isn't necessarily something you can simply “relax” on command. Pain can create a cycle Imagine inserting a tampon hurts. The next time you try, you naturally expect it to hurt. Your body may respond by tightening the pelvic floor muscles before you've even realised it. Then insertion hurts again. Over time, this can create a cycle: Pain → fear or anticipation → muscle tightening → more pain. Breaking this cycle often requires more than simply trying harder to relax. Does painful tampon use mean something is wrong? Not necessarily, but persistent pain deserves attention. If tampon use has always been painful, has suddenly become painful, or is becoming increasingly difficult, it's worth finding out why. A GP, gynaecologist or pelvic health physiotherapist can help identify potential contributors. How can pelvic floor physiotherapy help? A pelvic floor physiotherapist can assess whether your pelvic floor muscles are contributing to the pain. Depending on your symptoms and comfort level, treatment may include: Education about pelvic floor function Breathing and relaxation strategies Pelvic floor down-training Gentle manual therapy where appropriate Gradual desensitisation Advice around comfortable tampon insertion Strategies to reduce muscle guarding An internal examination is not automatically required. Your physiotherapist should explain your options and work within your comfort and consent. Don't force it If inserting a tampon is painful, don't keep pushing through significant pain. Pain is useful information. And if you're experiencing significant pain, burning, unusual discharge, bleeding or other new symptoms, speak with your GP or gynaecologist to rule out medical causes. Frequently Asked Questions Why does inserting a tampon hurt? Tampon insertion can hurt for many reasons, including pelvic floor muscle tension, vaginal dryness, irritation, infection, hormonal changes or vulval conditions. A healthcare professional can help identify the cause. Can a tight pelvic floor make tampons difficult to insert? Yes. If the pelvic floor muscles around the vaginal opening are overactive or unable to relax, insertion may feel painful, tight or blocked. Can pelvic floor physiotherapy help with painful tampon insertion? Yes. When pelvic floor muscle tension or poor relaxation is contributing to symptoms, pelvic health physiotherapy can help with relaxation, coordination and gradually reducing sensitivity and muscle guarding. The Bottom Line Tampon use shouldn't be something you have to grit your teeth through. If inserting a tampon is consistently painful, difficult or impossible, there may be a reason—and it's worth investigating. You don't need to simply “get used to it,” and you certainly don't need to push through pain. If painful tampon use is affecting your periods, exercise, swimming or everyday life, a pelvic health physiotherapist can help you understand whether your pelvic floor is contributing and work with you towards more comfortable, confident movement.
By Nicola Andreacchio September 14, 2026
If you've ever wondered whether you need to douche before anal sex, you're certainly not alone. For some people, rectal douching can help them feel cleaner, more comfortable and more confident before intimacy. But there's one important thing that's often misunderstood : Douching doesn't protect you from HIV or STIs. In fact, frequent or forceful douching can irritate the delicate lining of the rectum and potentially increase the risk of infection. So, if you choose to douche, what do you actually need to know? What exactly is rectal douching? Rectal douching involves putting water or another fluid into the rectum and then releasing it, usually to clear stool from the lower part of the bowel. People may choose to douche before anal sex because it can help them feel more comfortable or confident. And that's a perfectly valid personal choice. The important thing is understanding tha t douching is about comfort and preparation — not protection from infection. Does douching reduce the risk of HIV or STIs? No. One of the biggest myths about rectal douching is that it "washes away" bacteria or viruses and therefore makes sex safer. Unfortunately, that's not how it works. The lining of the rectum is delicate. Douching can cause irritation and, particularly when it's frequent or forceful, may cause small areas of damage to the tissue. This can potentially make it easier for infections to enter the body. So while you may feel cleaner afterwards, you aren't necessarily safer. Why can douching increase risk? Think about the inside of your rectum like a delicate lining that you don't want to scrub or strip. Douching can: · Irritate the rectal lining · Cause small tears or inflammation · Disrupt the natural environment of the rectum · Potentially make the tissue more vulnerable to infection The risk may be greater when douching involve s high pressure, larger volumes or repeated flushing. And this is where the idea of "more cleaning = better" can actually backfire. Your rectum doesn't need to be spotless. But isn't douching helpful for some people? It can be. Some people choose to douche because it helps them: · Feel more confident · Feel more comfortable during intimacy · Reduce anxiety about mess · Feel prepared and in control These are real benefits for the person choosing to douche. The key is simply understanding what douching can and can't do. It may help you feel more comfortable. It does not prevent HIV or STIs. Is there a "right" way to douche? There's no universally agreed safe volume or frequency for rectal douching. However, it is recommended to use bulb douching systems of up to 300 ml ideally no more than 2 flushes as gentle squeeze pressure. Keep the pressure low. Avoid forceful flushing or high-pressure systems. The rectal lining is delicate, and unnecessary pressure can cause irritation or injury. Never use household cleaning products such as: · Soap · Detergent · Bleach · Vinegar · Lemon juice These can irritate or chemically damage the rectal lining. Don't keep flushing. You don't need to keep douching until the water runs perfectly clear. Repeated flushing can increase irritation without necessarily giving you any additional benefit. Aim for gentle and minimal rather than repeated and forceful. What about using lubricant? Lubricant is an important part of safer and more comfortable anal sex. But not all lubricants are the same. Some products can be more irritating to sensitive tissue, particularly highly concentrated or hyperosmolar lubricants . Silicone-based lubricants can be a good option for anal sex because they provide long-lasting lubrication and don't dry out as quickly. The most important thing is choosing a product that's designed for the type of sexual activity you're having and using plenty of it. When should you avoid douching? It's best to avoid douching if you're already experiencing: · Anal or rectal pain · Rectal bleeding · An anal fissure · Painful haemorrhoids · Significant irritation or sores If something is already irritated, flushing it isn't likely to help. If you're experiencing ongoing pain, bleeding or other symptoms, it's worth getting assessed rather than trying to manage the problem yourself. What actually reduces the risk of HIV and STIs? This is the really important part. Douching isn't a safer-sex strategy. Depending on your circumstances, strategies that can actually reduce your risk include: Condoms - Condoms can reduce the risk of HIV and many other STIs when used correctly. PrEP - PrEP, or pre-exposure prophylaxis, is highly effective at preventing HIV when taken as prescribed. If you're at risk of HIV, talk to your GP or sexual health service about whether PrEP is right for you. Regular STI testing - Regular sexual health checks are important, particularly if you have new or multiple partners. Communication - Talking openly with your partner about sexual health, testing, condoms and PrEP can help you make informed decisions about your sexual health. What about microbicide enemas? You may have heard about research into rectal microbicides, including products containing tenofovir. This is an interesting area of research, but these products are not currently an established replacement for proven HIV prevention strategies such as PrEP and condoms. Frequently Asked Questions Does rectal douching prevent HIV? No. Douching does not prevent HIV and may potentially increase vulnerability to infection by irritating or damaging the rectal lining. Does douching prevent STIs? No. Douching doesn't protect against STIs. In fact, irritation or damage to the rectal lining may potentially increase the risk of infection. How often should I douche? There's no established "safe" frequency. As a general harm-reduction approach, less frequent and gentler is better than repeated, forceful douching. Can I use soap or other cleaning products? No. Soap, detergents, bleach, vinegar, lemon juice and other household products can irritate or damage the delicate rectal lining. Stick with plain, lukewarm water if you choose to douche. Do I need to douche before anal sex? Not necessarily. Whether you douche is a personal choice. Some people find it helps them feel more comfortable or confident, while others don't feel the need to do it at all. You don't have to douche to have enjoyable anal sex. The Bottom Line Douching is about comfort — not protection. If you choose to douche, keeping it gentle, simple and infrequent can help minimise irritation to the delicate rectal tissue. But don't rely on douching to protect you from HIV or STIs. Condoms, PrEP and regular STI testing are far more important when it comes to safer sex. And remember: your body doesn't need to be perfectly clean to enjoy sex. If you're experiencing pain, bleeding, irritation or ongoing anal or rectal symptoms, a pelvic health physiotherapist or healthcare professional can help you work out what's going on.
By Dennise Smith September 7, 2026
Hot flushes get all the attention. Mood changes, irregular periods and night sweats are talked about more than ever. But there's one symptom that still catches many women completely off guard: Changes in bladder function. Many women in their 40s and 50s suddenly find themselves planning every outing around the nearest toilet, waking multiple times overnight to wee, or leaking urine when they laugh, cough or exercise. If this sounds familiar, you're not imagining it—and you're certainly not alone. Bladder symptoms are common during perimenopause, but they're often overlooked or dismissed as "just getting older." The good news? They're common, but they're not something you have to put up with. Can perimenopause really affect your bladder? Yes. Perimenopause is the transition leading up to menopause, during which hormone levels—particularly oestrogen—begin to fluctuate. Oestrogen plays an important role in maintaining the health of the bladder, urethra and surrounding tissues. As hormone levels change, some women notice new bladder symptoms, even if they've never had problems before. Common bladder changes during perimenopause Every woman experiences perimenopause differently, but some of the most common bladder symptoms include: You're going to the toilet more often Do you find yourself needing to wee every hour or two? You may also notice you're planning car trips around toilet stops or always checking where the nearest bathroom is. While this can happen for many reasons, hormonal changes during perimenopause can make the bladder feel more sensitive. You suddenly can't "hold on" One minute you're fine. The next minute you're desperately searching for the nearest toilet. This sudden, difficult-to-ignore urge to urinate is known as urgency, and it can become more noticeable during perimenopause. You leak when you cough, laugh or exercise Bladder leakage isn't an inevitable part of ageing. Many women notice stress urinary incontinence during perimenopause, particularly if they've previously been pregnant, had vaginal births, or participate in high-impact exercise. These symptoms are often very treatable. You're waking several times overnight to wee Getting up once occasionally isn't unusual. But if you're waking multiple times every night, it may be affecting your sleep, energy and overall wellbeing. Nocturia (waking overnight to urinate) can have many causes, including bladder changes associated with ageing and hormonal fluctuations. It's worth discussing persistent symptoms with your healthcare provider to identify the underlying cause. Recurrent urinary tract infections (UTIs) Some women notice they begin experiencing UTIs more frequently during perimenopause. Changes in oestrogen levels can affect the tissues around the urinary tract and alter the protective environment of the vagina, increasing susceptibility for some women. If you're experiencing recurrent infections, it's important to seek medical assessment. Is it just a weak pelvic floor? Not necessarily. One of the biggest myths is that every bladder problem means your pelvic floor is weak. In reality, bladder symptoms can result from a combination of factors, including: hormonal changes changes to the bladder lining pelvic floor muscles that are weak pelvic floor muscles that are overactive or don't relax well constipation bladder habits fluid intake certain medications other medical conditions. That's why the same treatment doesn't work for everyone. What can a pelvic floor physiotherapist do? A pelvic floor physiotherapist looks beyond the symptom itself. Your assessment may include: pelvic floor muscle strength muscle relaxation and coordination bladder habits fluid intake bowel function breathing patterns movement and exercise lifestyle factors. Treatment is personalised and may involve: pelvic floor muscle training (when appropriate) bladder retraining urgency management strategies advice on bladder-friendly habits breathing and pressure management education about lifestyle factors that may influence symptoms. If your physiotherapist believes hormonal changes are contributing significantly to your symptoms, they may also recommend discussing treatment options with your GP or menopause specialist. Don't cut back on water A common response to bladder urgency is to drink less. Unfortunately, this can sometimes make things worse. Concentrated urine can irritate the bladder lining, increasing urgency and frequency. Rather than drastically reducing your fluid intake, it's better to identify the underlying cause of your symptoms and develop a management plan that's right for you. Frequently Asked Questions Can perimenopause cause an overactive bladder? Yes. Hormonal changes during perimenopause can contribute to bladder urgency and frequency in some women. However, other conditions can cause similar symptoms, so an assessment is important to identify the underlying cause. Why am I suddenly leaking urine in my 40s? Bladder leakage during your 40s can be influenced by hormonal changes, pregnancy history, pelvic floor function, ageing and lifestyle factors. Many women benefit from assessment and treatment by a pelvic floor physiotherapist. Will bladder problems improve after menopause? Some symptoms improve over time, while others may persist without treatment. The outlook depends on the underlying cause. Early assessment can help identify strategies to improve bladder function and quality of life. The Bottom Line Perimenopause can bring unexpected changes—but constantly thinking about your bladder doesn't have to become your new normal. Whether you're leaking urine, rushing to the toilet, waking overnight or simply feeling that your bladder has "changed," there are effective treatment options available. You don't need to wait until symptoms become severe to seek help. If bladder changes are affecting your confidence, sleep or daily life, our pelvic health physiotherapists can help identify what's contributing to your symptoms and create a personalised treatment plan, so you can get back to living without your bladder calling the shots.
By Derryn Pert September 3, 2026
When you hear the words "pelvic floor," what comes to mind? For many people, it's pregnancy, childbirth or women's health. But here's something that surprises many of our male patients: Men have a pelvic floor too. And when these muscles aren't working as they should, they can contribute to a wide range of symptoms that are often overlooked, misdiagnosed or simply accepted as "part of getting older." The good news? Many pelvic floor issues are treatable, and you don't have to live with them. What is the pelvic floor? The pelvic floor is a group of muscles that sits at the base of the pelvis like a supportive hammock. In men, these muscles help: support the bladder and bowel control urination and bowel movements contribute to sexual function provide stability for the pelvis and lower back coordinate with your breathing and core muscles. Like any other muscle group, they can become weak, overactive, poorly coordinated or painful. 1. You're going to the toilet "just in case" Do you find yourself using the toilet before leaving the house, before meetings or whenever you see a bathroom—even when you don't really need to go? While this habit can seem harmless, it may contribute to bladder urgency over time. If you're frequently: rushing to the toilet needing to urinate often waking multiple times overnight struggling to hold on, your pelvic floor and bladder coordination may be worth assessing. 2. You leak urine Bladder leakage isn't just a women's issue. Some men notice leakage: after prostate surgery during exercise when coughing or sneezing after they've finished urinating (post-void dribbling) without warning. Many men are embarrassed to bring this up, but it's a common reason to see a pelvic floor physiotherapist. 3. You have ongoing pelvic pain Pain in the pelvis isn't always coming from the prostate. Persistent pain may be felt in the: perineum (between the scrotum and anus) tailbone lower abdomen groin penis testicles hips. In some men, overactive or sensitive pelvic floor muscles contribute to these symptoms. 4. You struggle to empty your bowels Your pelvic floor muscles need to relax for a bowel motion to pass comfortably. If they don't coordinate well, you may experience: constipation straining incomplete emptying prolonged time on the toilet. Improving pelvic floor coordination can be an important part of managing bowel symptoms. 5. Sitting is uncomfortable Does sitting for long periods increase your discomfort? Persistent aching around the tailbone, deep pelvis or perineum may be related to several different conditions, including pelvic floor dysfunction. A comprehensive assessment can help identify contributing factors. 6. Sex has become painful—or isn't functioning the way it used to The pelvic floor also plays an important role in sexual health. Pelvic floor dysfunction may contribute to: pain during or after ejaculation erectile dysfunction in some cases reduced confidence pelvic muscle tension during intimacy. Because sexual function can be influenced by many factors—including cardiovascular health, hormones, medications and psychological wellbeing—it's important to have a thorough assessment to understand what's contributing to your symptoms. 7. You've had prostate surgery Pelvic floor physiotherapy is commonly recommended before and after prostate surgery. Treatment may help improve: bladder control confidence returning to activity pelvic floor muscle coordination recovery following surgery. If you're preparing for prostate surgery, seeing a pelvic floor physiotherapist beforehand can help you learn the correct exercises and what to expect during recovery. It's not always about weakness One of the biggest misconceptions is that pelvic floor problems are always caused by weak muscles. In reality, some men have pelvic floor muscles that are too tight, don't relax well or aren't coordinating properly. That's why doing pelvic floor exercises you find online isn't always the best approach. A personalised assessment is the safest way to determine what your body actually needs. When should you see a pelvic floor physiotherapist? Consider booking an assessment if you have: bladder leakage urinary urgency or frequency constipation or straining pelvic or tailbone pain pain around the penis, scrotum or perineum pain with ejaculation difficulty returning to exercise after prostate surgery ongoing symptoms that aren't improving. Many men wait months—or even years—before seeking help because they assume these symptoms are normal. They're common, but they aren't something you have to simply live with. Frequently Asked Questions Do men have pelvic floor muscles? Yes. Men have pelvic floor muscles that support the bladder and bowel, assist with continence, contribute to sexual function and work with the core muscles to provide stability. Can a pelvic floor physiotherapist help men? Absolutely. Pelvic floor physiotherapists assess and treat a range of conditions affecting men, including bladder leakage, pelvic pain, constipation, and recovery after prostate surgery. Should men do Kegel exercises? Not always. While pelvic floor strengthening is beneficial for some men, others have muscles that are overactive or poorly coordinated. An assessment helps determine whether strengthening, relaxation or a combination of approaches is most appropriate. The Bottom Line Pelvic floor problems are far more common in men than many people realise. Whether it's bladder leakage, pelvic pain, constipation or changes in sexual function, these symptoms are not something you should ignore or simply put down to ageing. The first step is understanding what's causing your symptoms. From there, a pelvic floor physiotherapist can develop a personalised treatment plan to help you regain confidence, comfort and control. You don't have to put up with pelvic floor symptoms just because you're a man. If something doesn't feel right, book an assessment with one of our pelvic health physiotherapists and take the first step towards getting back to doing the things you enjoy.